AZ & TX Advanced Imaging

Radiology Protocols

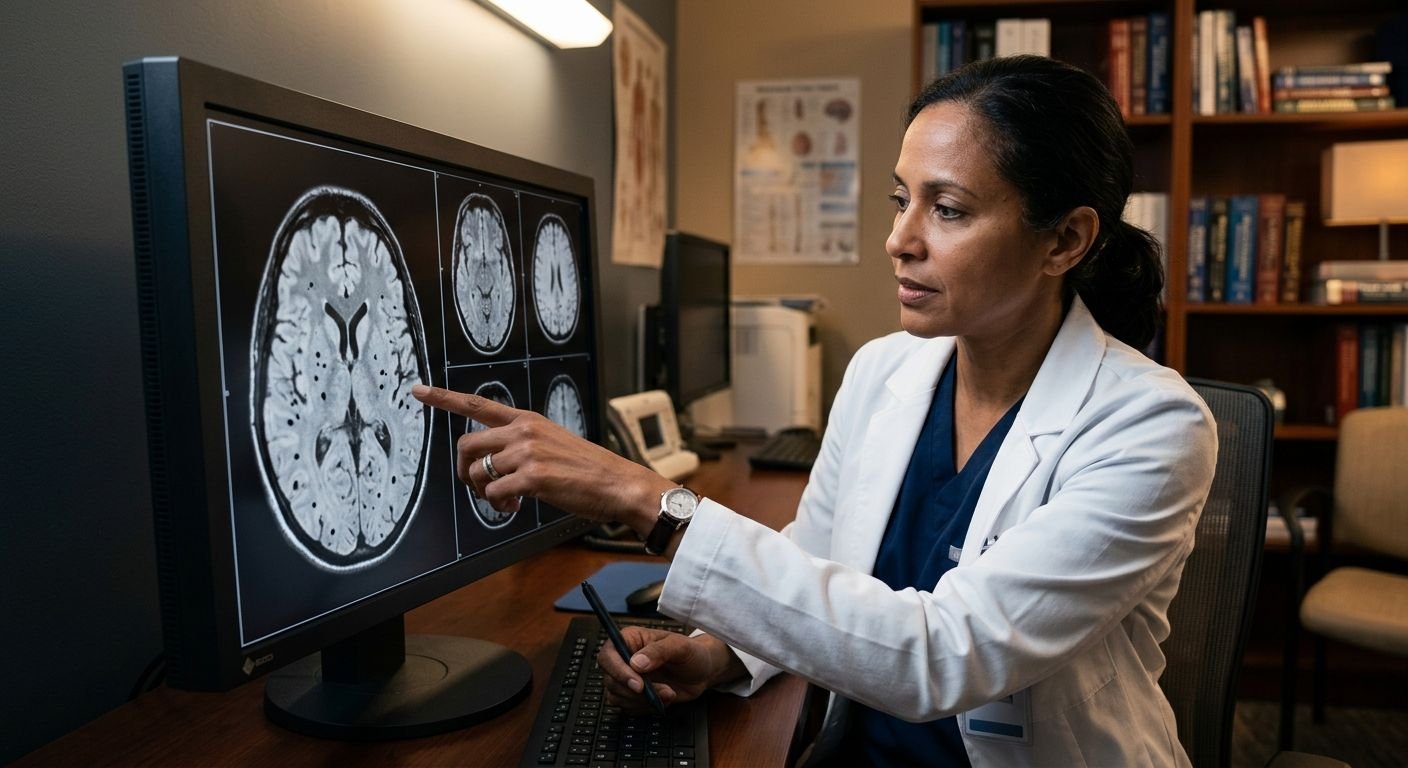
Neuroradiologist examining susceptibility weighted imaging brain scans on a monitor in a modern reading room
Advanced MRI Technology, Radiology Protocols, Traumatic Brain Injury (TBI)

Susceptibility-Weighted Imaging in TBI MRI: Uses and Limits

Susceptibility-weighted imaging (SWI) is an MRI technique that can contribute information about susceptibility differences, including some blood products. Its findings require interpretation within the clinical assessment. In this article Avoid universal detection claims What imaging can and cannot establish Discuss the ordered protocol Plan for results and follow-up Avoid universal detection claims SWI can be useful in evaluating microhemorrhages in appropriate circumstances, but it cannot guarantee that every clinically significant microbleed or traumatic injury will be detected. No fixed 50% detection or sensitivity advantage is asserted here. A numerical comparison requires the exact study population, scanner, acquisition technique and comparison method. What imaging can and cannot establish A concussion assessment starts with a healthcare provider’s clinical evaluation. Brain imaging is not routinely needed to identify every mild TBI or concussion; the clinician selects tests when they address a specific concern. CT and MRI can help evaluate some structural injuries, but they cannot detect every TBI. A normal scan does not by itself exclude a concussion, and an abnormality must be interpreted in clinical context. Advanced methods such as DTI, SWI and quantitative analysis have different uses and limitations. Do not treat a technique, software result or marketing protocol as a stand-alone diagnosis or a guarantee that subtle injury will be found. Discuss the ordered protocol Ask the ordering clinician why SWI or another advanced sequence is being requested and what limitations should be expected. Confirm that the specific protocol is available at the selected center. A report should describe findings and uncertainty rather than turn imaging into automatic proof of symptoms, accident causation or a legal outcome. Plan for results and follow-up Ask when the report is expected, how it will reach the ordering clinician and whom to contact if it has not arrived. Routine report timing depends on the study and review process; no fixed delivery deadline is promised here. The treating clinician interprets the report alongside symptoms, examination findings and prior studies. Imaging does not by itself determine treatment, the cause of an injury or a legal outcome. Request a clinical follow-up plan. Questions about imaging or scheduling? Call 844-641-2111 or find a location to contact your preferred imaging center. Further reading TBI imaging: advanced techniques and evidence — RSNA TBI diagnosis and imaging limitations — FDA
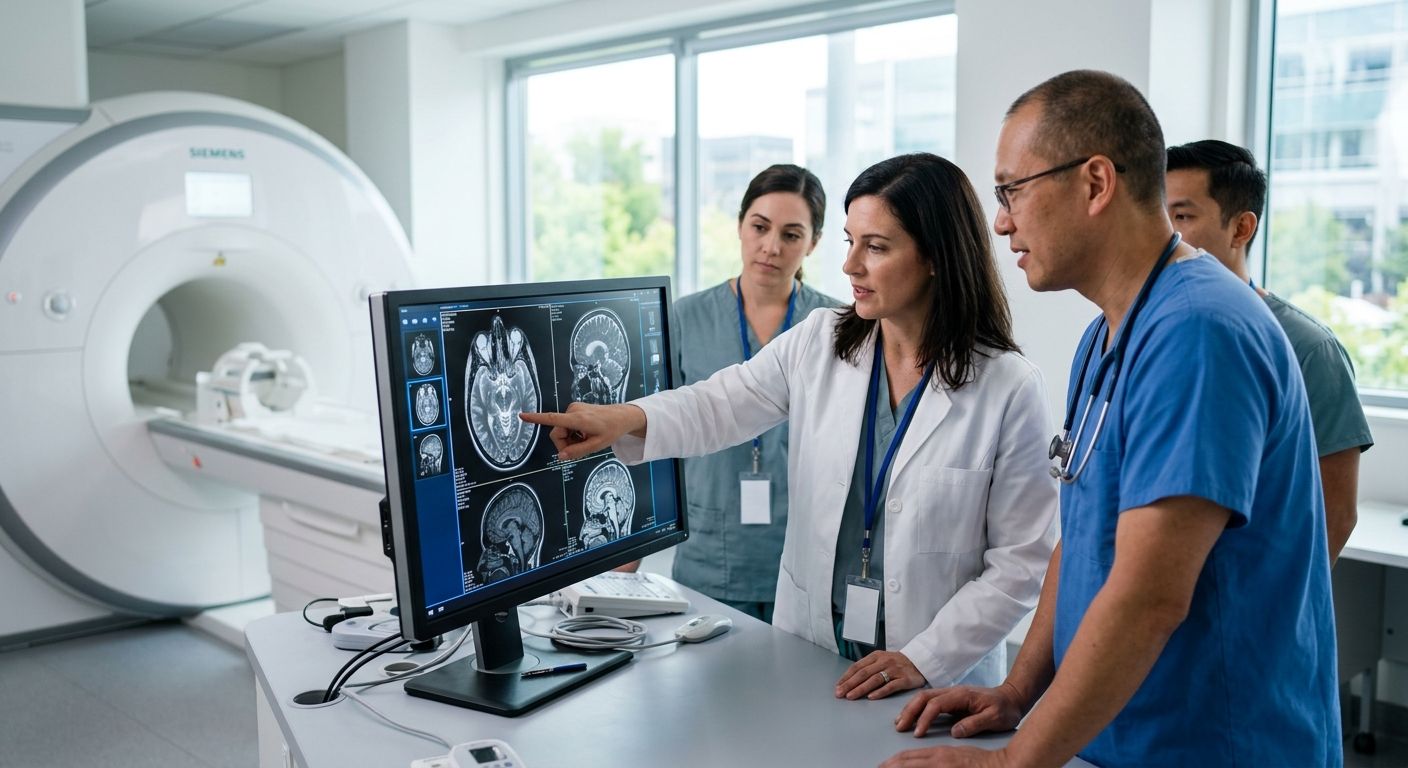
Radiology team discussing MRI brain scans on a high-resolution monitor in a modern imaging center, with a specialist pointing to a finding and a referring physician observing.
Medical-Legal Services, Radiology Protocols, Radiology Services

Radiology Report Turnaround: Planning Communication and Follow-Up

Report delivery depends on the examination, interpretation and communication process. Appointment access and scan completion are separate from the time a final report reaches the ordering clinician. In this article Ask for a realistic estimate Distinguish urgent findings from routine reporting Reduce avoidable communication gaps Ask for a realistic estimate Confirm when the report is expected, how it will be delivered and whether prior studies or additional review may affect timing. Ask which contact can check a missing report. No universal ACR requirement that every routine report be completed within 24–48 hours is asserted here. A local service target must be confirmed rather than treated as a guarantee. Distinguish urgent findings from routine reporting If symptoms require emergency assessment, seek urgent care rather than waiting for an outpatient report. Ask the treating clinician how time-sensitive findings and follow-up will be handled. Patients should not have to infer a diagnosis from scheduling messages. Arrange a discussion with the treating clinician to interpret the report and decide next steps. Reduce avoidable communication gaps Provide accurate ordering-clinician details and ask how prior examinations should be transferred. Confirm the appropriate records-delivery method and intended recipient. For authorized legal records requests, ask about the release process separately; there is no promise of instant law-firm portal access or legally decisive findings. Questions about imaging or scheduling? Call 844-641-2111 or find a location to contact your preferred imaging center.

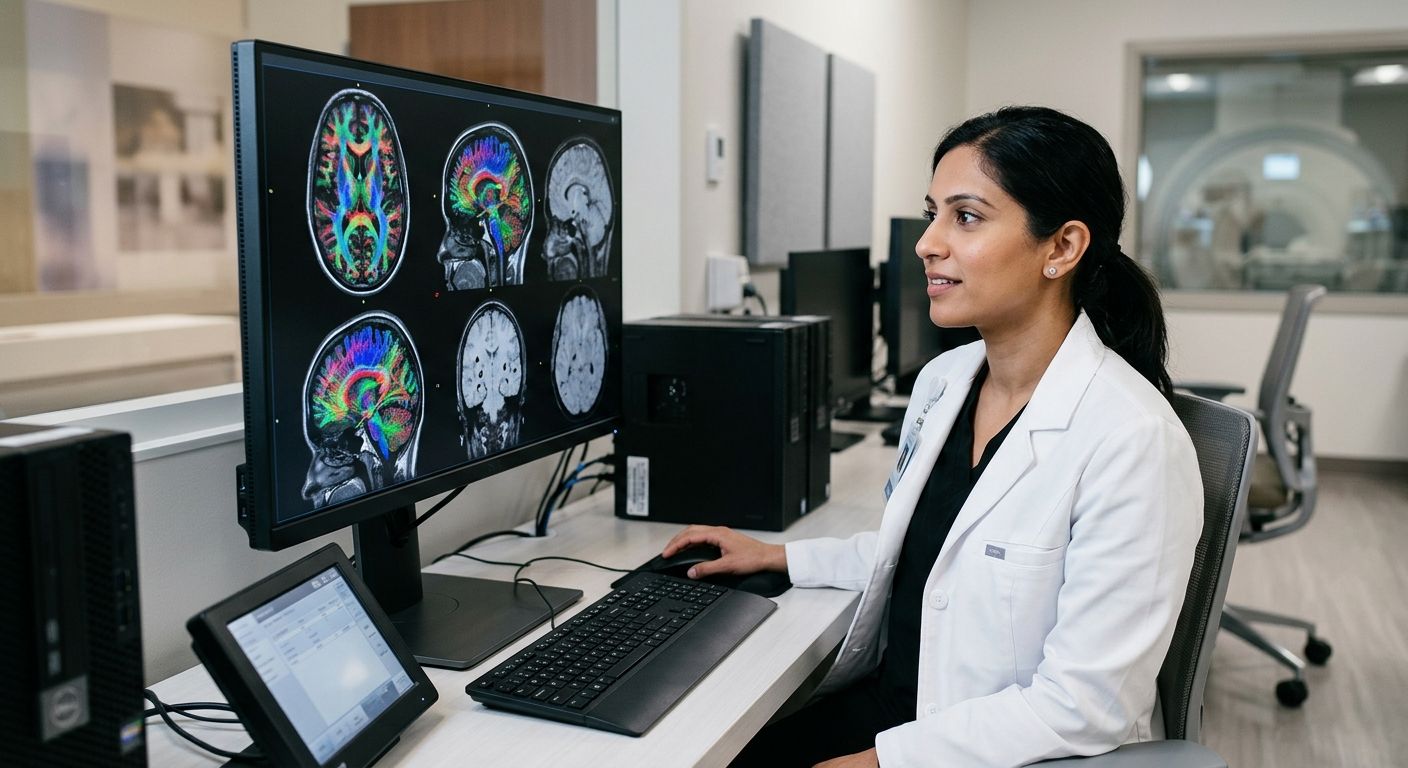
Board-certified radiologist reviewing advanced brain MRI scans on a large monitor in a modern imaging suite
Healthcare Legal Support, Medical Imaging Services, MRI & CT Diagnostics, Personal Injury Care, Radiology Protocols, Traumatic Brain Injury (TBI)

TBI Imaging: DTI, SWI and Clinical Limitations

Advanced MRI techniques should be discussed in the context of the clinical assessment and the evidence for the specific use. They are not universal screening tests for every head injury. In this article What imaging can and cannot establish Distinguish technique from diagnosis Confirm the actual study Plan for results and follow-up What imaging can and cannot establish A concussion assessment starts with a healthcare provider’s clinical evaluation. Brain imaging is not routinely needed to identify every mild TBI or concussion; the clinician selects tests when they address a specific concern. CT and MRI can help evaluate some structural injuries, but they cannot detect every TBI. A normal scan does not by itself exclude a concussion, and an abnormality must be interpreted in clinical context. Advanced methods such as DTI, SWI and quantitative analysis have different uses and limitations. Do not treat a technique, software result or marketing protocol as a stand-alone diagnosis or a guarantee that subtle injury will be found. Distinguish technique from diagnosis DTI examines water-diffusion characteristics, while SWI emphasizes magnetic-susceptibility differences. These techniques provide different information; neither should be advertised as proof of every subtle injury or automatic evidence of accident causation. RSNA’s TBI imaging review describes limitations in applying advanced techniques routinely to diagnosis or prognosis in an individual patient. Discuss the proposed use with an appropriately qualified clinician. Confirm the actual study Ask which sequences are ordered, where they can be performed and how the report will explain findings and limitations. This article makes no unsupported claim about a new 2026 AAN or CDC guideline. Plan for results and follow-up Ask when the report is expected, how it will reach the ordering clinician and whom to contact if it has not arrived. Routine report timing depends on the study and review process; no fixed delivery deadline is promised here. The treating clinician interprets the report alongside symptoms, examination findings and prior studies. Imaging does not by itself determine treatment, the cause of an injury or a legal outcome. Request a clinical follow-up plan. Questions about imaging or scheduling? Call 844-641-2111 or find a location to contact your preferred imaging center. Further reading About mild TBI and concussion — CDC TBI diagnosis and imaging limitations — FDA TBI imaging: advanced techniques and evidence — RSNA

Scroll to Top